Neck Pain and Physical Response: What Can Measurement Add?
The neck is a difficult region to reason about from symptoms alone: the reported pain and the physical response are two different kinds of information, and one does not automatically explain the other. The pain score is the person's reported experience. The physical measurement is what the instrument records. Both can be compared between baseline and retest — each on its own terms.
Start With the Baseline
The baseline is a defined neck-region movement task — a repeated rotation, flexion-extension sequence or supported posture task — performed the same way each time. Two records are made: how the person reports their pain, and how their body currently moves through the task. The person becomes their own comparison. See Why Establish a Baseline Before Trying to Change Pain?
What Can the Sensor Sling Measure?
Using the I AM 900 Sensor Sling head/neck configuration, supported physical measurements can be recorded during a defined assessment. Where the instrument configuration supports it:
- Sling pressure — distributed pressure recorded at relevant Sling measurement locations.
- Pressure distribution — how the recorded pressure is distributed across the relevant sensor locations through the task.
- Angle / orientation — orientation information supported by the sensor configuration.
- Timing and sequence — when measurable events occur, and the order in which they occur.
- Repeatability — how consistently the recorded response appears across comparable trials.
- Proximal/distal relationships where genuinely measured — where more than one Sling location is configured for the task, relationships between the recorded measurements at different locations are observations about the recorded data — not anatomical claims.
Each of these is a supported measurement of the physical response during the task — nothing more, and no diagnostic claim.
What Measurement Is Not Taken to Mean
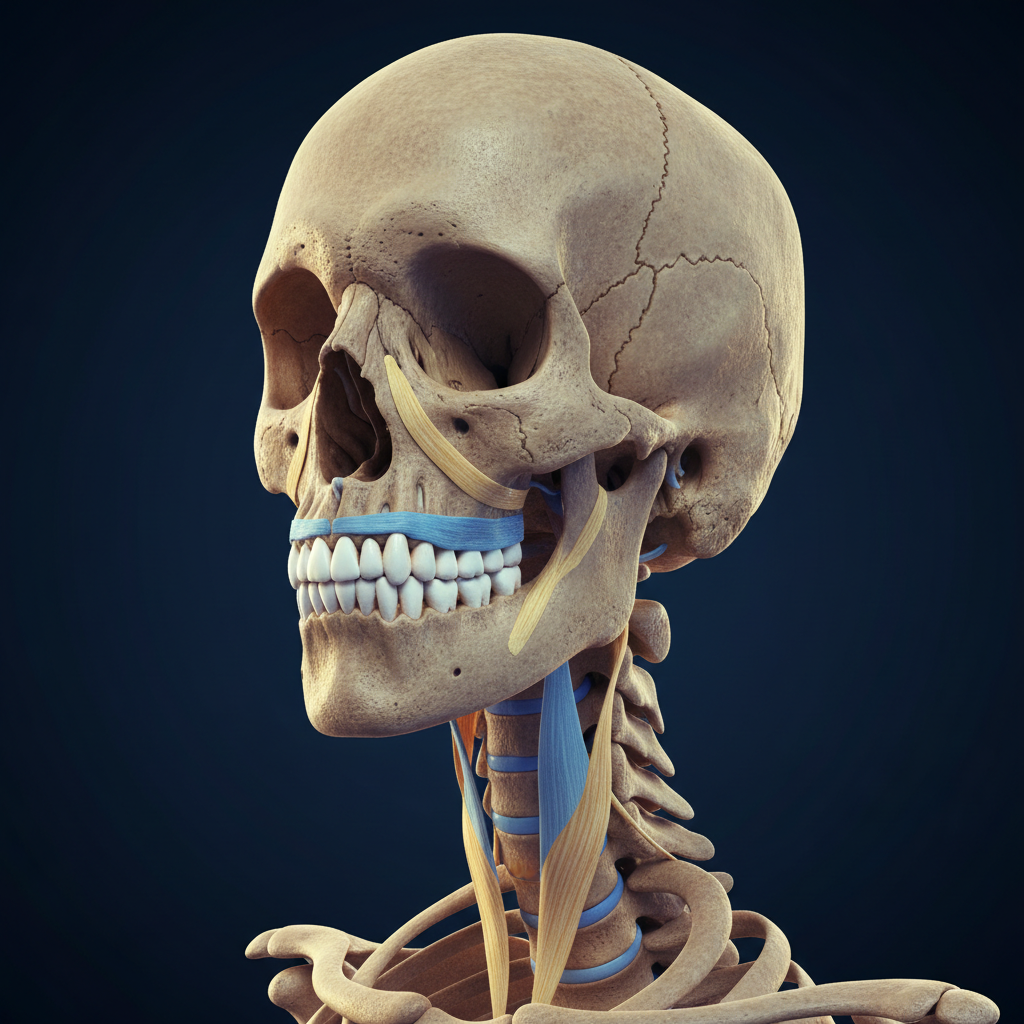
Nothing in the recorded set is inferred as anatomical pathology. Recorded pressure, distribution, angle, timing or sequence do not diagnose disc or joint pathology, do not identify a nerve or structural cause, and do not explain why the person reports pain. The measurement records the physical response; clinical questions belong with qualified assessment, which remains a separate process. For the anatomy and condition context, see Neck Pain and Whiplash and Cervical Disc Degeneration.
Change the Input, Retest, Compare
Calibration applies a defined, practitioner-directed change to the input or conditions of the task (what calibration means). The same task is then repeated under the same conditions, and the retest is compared with the baseline on both tracks: the reported pain and the physical measurement. The difference is information — it does not by itself establish why anything changed, and it is not a guarantee of pain improvement. The retest logic is set out in Why Retesting Matters in Pain.
Where This Fits
The pain pathway — including recorded outcomes — is at /pain; the method at /method; the calibration process at /calibrate; the instrument at I AM 900 Sensor Sling. Related reading: Pain Score vs Physical Measurement, Pressure Distribution and Pain, and Using the I AM 900 Sensor Sling to Measure Physical Response.